While in college, I took courses in finite mathematics and calculus, earning an A in both. But finite mathematics came much more naturally to me. The best way I can explain the difference is through baseball. When a hitter struggles with a fastball, it can look like a pea coming toward the plate. For the best hitters, that same fastball can look as big as a basketball. Finite mathematics was my basketball. I could see the numbers, understand their relationships, and work through problems almost instinctively.
Finite mathematics deals with quantities we can count, organize, and compare. Calculus examines how those quantities change and how different variables influence one another over time. Both are useful, but understanding the full cost of pharmacy benefits requires more than calculating discounts and measuring performance against contractual guarantees. Employers must understand how price, utilization, drug mix, and member cost share interact to influence spending. A program can meet its pricing guarantees while total costs rise, or miss a guarantee while delivering a substantial reduction in spending. Understanding the difference is where meaningful oversight begins.
What the Numbers Reveal
After we submitted a proposal to a brokerage firm, a senior leader questioned why we had included cost per member per month, or PMPM. His reaction surprised me. We were proposing a pharmacy benefit and PMPM helped explain its financial impact relative to the population being covered. Including it seemed fundamental. That conversation illustrated how deeply our industry’s evaluation process centers on pricing terms, even when the employer’s objective is to understand and manage the cost of the benefit.
A second experience made the distinction even clearer. A partner at a brokerage firm shared a performance review following a new client’s first three months with us. We had met all but one contractual guarantee, falling short on 30 day retail brand prescriptions. The initial exchange did not include total cost or PMPM, so I brought the spending trend into the discussion.
The incumbent PBM’s year end cost was approximately $120 PMPM. By June, reported monthly cost under our program had fallen to approximately $51 PMPM, about 57 percent below that baseline. Those figures excluded administration fees and rebates, so they were not a complete measure of net cost. They were nevertheless a significant part of the financial picture.
The missed guarantee deserved attention. A provider should be accountable for its contractual commitments regardless of the overall financial outcome. But an assessment that highlighted the shortfall without examining the spending trend would have been incomplete. The partner agreed that the broader financial result mattered and also asked about the member experience. That conversation appropriately expanded to consider whether the promised pricing had been delivered, how costs were changing, and what members were experiencing.
Four Factors That Shape Cost
Brokers and consultants are good at measuring performance against guarantees because the exercise is finite. There is a target, an actual result, and a difference between them. Evaluating cost requires a broader analysis of four factors:
Price: What is paid for each prescription.
Utilization: How much medication members use.
Drug mix: Which medications members use, including the balance among generic, brand, and specialty drugs.
Member cost share: How the expense is divided between the employer and its members.
A stronger discount can be offset by a more expensive drug mix, while higher member cost share can lower employer spending without reducing total cost. Recognizing those relationships takes more than access to a report. It requires ongoing education and the ability to interpret the data, question assumptions, and distinguish a pricing improvement from an improvement in overall cost. Employers should expect their advisors to bring that depth of understanding to every review.
A Clear Standard for Executive Review
Meaningful comparisons require consistent definitions. Every review should specify whose spending is measured, how administration fees and rebates are treated and whether the covered population has changed. It should also distinguish a monthly spending trend from savings measured across a full quarter or year. Those details give executives a sound basis for judging the result.
Require every pharmacy benefits review to answer three questions: Did the provider meet its guarantees? What happened to total cost and PMPM? What drove the result? Hold providers accountable for their pricing commitments and for explaining the financial outcome. Until all three questions are answered, the review is incomplete.
Transparency is becoming a legal requirement across pharmacy benefits. The Consolidated Appropriations Act, 2026 added federal PBM reporting obligations that take effect in later plan years.¹ Minnesota already requires specified disclosures to plan sponsors on request.² Requirements and effective dates vary, but the direction is clear. Employers are gaining rights to see more of how their benefits operate, and they need to consider what they can do with that information. Control is the new currency in pharmacy benefits management.
Disclosure alone does not guarantee a more valuable benefit. A report may help an employer identify a cost issue or understand a financial arrangement, but improvement still requires a decision and the ability to carry it out. Buyers need authority to evaluate alternatives, make changes, and hold their partners accountable. Transparency and control create the opportunity for better results when the employer understands the information and uses it.
A client recently selected us specifically because of the control our pharmacy benefits administration model would give them. That control became tangible when a copay waiver program came up as a possible addition to their benefit design. The client did not understand how the program worked, so it was explained. The final decision about whether to include it remained theirs.
The client’s selection connects control to purchasing value. They chose a model that preserved their authority, then encountered a decision where that authority mattered. The explanation supported their ability to evaluate the option, while the choice stayed with them. Employers should assess that combination when deciding what an arrangement is worth to their organization.
Control looks like having usable information and knowing which decisions the employer can make. It includes understanding how benefit changes affect costs, guarantees, and members, as well as being able to verify contractual performance and seek a remedy. Buyers should ask how a recommendation becomes an approved change and who has authority at each step. A transparent explanation becomes more useful when it supports a choice the employer can exercise.
The buying committee needs more than familiarity with PBM terminology to use that control. Finance should understand cost assumptions and cash flow, including payment and rebate timing. Benefits leaders should understand employee access and disruption, while procurement and legal connect commitments to contractual terms. Clinical advisers can evaluate treatment considerations. The committee should share enough knowledge to explain material tradeoffs and identify where further expertise is needed.
Securing control begins before selecting a vendor. Mark Cuban challenges the practice of announcing a winner before negotiating the contract.³ Megan Dorrell, PharmD, describes negotiating client-specific agreements before PBM selection.⁴ Their arguments put contract terms inside the competitive decision. Buyers can evaluate the proposed price alongside the rights that will govern the relationship, while alternatives remain available.
The National Alliance’s employer PBM playbook provides guidance on making those rights concrete.⁵ Employers should translate their priorities into requirements that bidders must address. Five areas deserve attention before selection:
Usable information: Specify required claims data, disclosures, delivery timing, and access for independent advisers.
Clear economics: Define pricing, fees, rebates, payment timing, and how guarantees will be measured.
Decision authority: Establish which benefit changes the employer can make and their contractual consequences.
Independent verification: Secure audit rights and remedies for identified shortfalls.
Adaptability: Negotiate workable market checks and clear terms for changing services or ending the relationship.
The committee also needs to agree on what the benefit should accomplish. Priorities for cost, quality, access, and employee impact provide a basis for evaluating recommendations. Employers should assess their internal expertise and identify who will manage the arrangement after implementation. An adviser’s compensation, relevant relationships, and oversight responsibilities belong in that assessment.⁶
Finalists should demonstrate how the proposed arrangement would handle a real benefit decision. Ask how they would explain a program, provide supporting information, identify tradeoffs, and implement the employer’s choice. Determine whether the decision would affect pricing or guarantees and carry important commitments into the contract. The exercise should show whether the employer’s expected control will be usable.
Once those rights are secured, give someone responsibility for exercising them. Review spending, investigate access problems, and check performance against the agreement. When costs rise, examine whether price, drug mix, or utilization is driving the change before choosing a response. Evaluate approved changes against plan spending, employee costs, access, and treatment continuity.
As transparency becomes an expected part of the benefit, employers should examine the authority that accompanies it. Our client’s experience shows why decision ownership belongs in the purchasing conversation. Information helped the client evaluate a proposed program, and control preserved their choice. Better value comes from putting both to work and checking whether the decisions produce the results the benefit was designed to deliver.
During a recent finalist presentation a PBM consultant asked about our biosimilar strategy. I explained that our review includes drug monographs along with the product label and available clinical trial data. We assess which patients are appropriate candidates. Our Pharmacy and Therapeutics committee then determines whether the product belongs on the formulary. Among clinically appropriate options we look for the most cost effective drug therapy to avoid the hidden cost of biosimilar rebates.
The consultant followed up, “What about the rebates?” My response was straightforward. We’re not chasing rebates. Once our clinical review establishes which therapies are appropriate we prioritize the lowest cost at the point of sale with savings that reach the patient. A drug can look attractive on a rebate report while leaving an employee paying substantially more to fill the prescription.
FDA approved biosimilars have no clinically meaningful differences in safety and effectiveness from their reference products.¹ Our clinical review builds on that foundation to assess how each product fits the patients we serve. We then evaluate the financial impact on both the employer and the employee. The rebate amount alone cannot tell us which option delivers the best value.
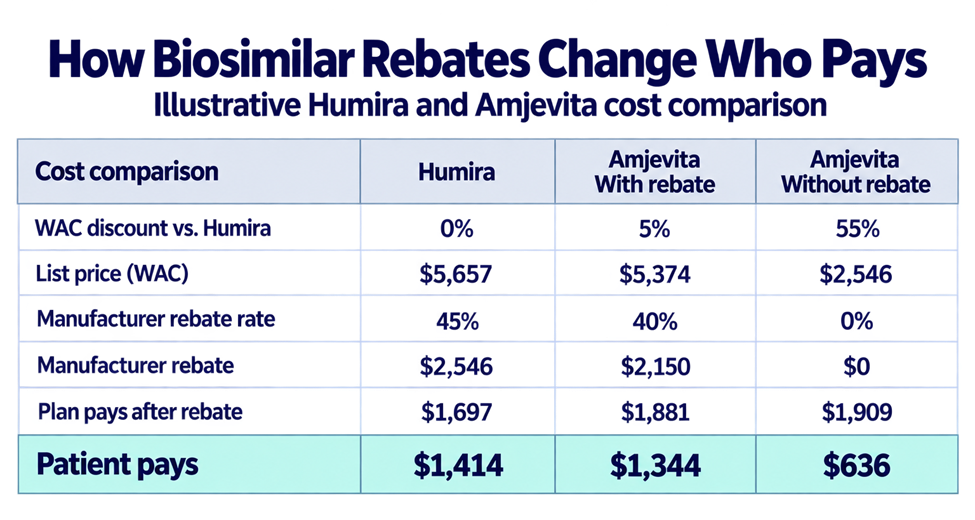
The Biosimilars Council illustrates this problem through a comparison of Humira and two pricing options for its biosimilar Amjevita. One option carries a higher list price with a substantial rebate. The other offers a much lower list price without a rebate. The difference becomes clear when we separate what the plan pays from what the patient pays.²
Rebated Amjevita saves the plan $28. The patient pays $708 more.
The rebated Amjevita option saves the plan $28 while the employee pays $708 more. An employer looking only at its own net expense might select that option. An HR leader looking at the employee’s experience has reason to challenge it. A modest reduction in the employer’s net cost does not justify a substantial increase in the employee’s cost.
That additional expense can become a barrier to treatment. Research on specialty medications has found that higher patient costs are associated with greater prescription abandonment.³ These are prescriptions that patients never pick up. Employers evaluating pharmacy savings need to consider whether employees can afford to begin and continue treatment.
The outcome depends on the benefit design. Fixed copays and manufacturer assistance can change the comparison. Deductibles and annual spending limits also affect what employees owe. Employers need an analysis using their actual benefits and claim prices that shows both patient costs at the pharmacy counter and plan costs after all rebates and fees.
Private label biosimilars add another financial relationship to examine. CVS Health owns Cordavis. Quallent operates within the same corporate family as Express Scripts. These businesses give the parent company a financial interest in products its PBM helps select for coverage. The FTC documented the largest PBMs’ expansion into private labeling and raised concerns about incentives to favor affiliated businesses.⁴
Formulary placement gives these arrangements their commercial power. CVS Caremark removed Humira from its major national commercial template formularies in April 2024 while expanding biosimilar coverage.⁵ CVS also markets a version of Hyrimoz through Cordavis.⁶ Express Scripts announced Humira exclusions on its largest commercial formularies for 2025 with alternatives that included products supplied through Quallent.⁷ These decisions can direct prescription volume toward products in which the PBM’s corporate family has a financial interest.
For an employer buyer the question is whether that preferred product offers the best available value. A substantial discount from Humira does not answer that question. A private label biosimilar can cost less than the reference drug and still cost more than another clinically appropriate option. The Amjevita example demonstrates why the comparison matters but does not establish the economics of any particular private label arrangement.
A 2025 employer case brings this purchasing decision into focus. Pharmacy Benefit Forensics reports that an employer coalition recommended a biosimilar from a PBM affiliated manufacturer while retaining rebates. The consultant identified alternative interchangeable biosimilars without rebates that it estimated would save the employer more than $8 million annually. According to the firm the employer changed its formulary and realized savings in 2025. The published account does not identify the employer or provide the underlying calculations or employee costs. It offers a relevant example of why employers need to evaluate alternatives even when a rebate appears attractive.⁸
The potential employer harm includes paying more than necessary and losing access to less expensive alternatives under the adopted formulary. Employers may also lack visibility into earnings retained by an affiliated distributor or specialty pharmacy. A rebate pass-through promise does not automatically reveal those earnings. Contract terms may further complicate the decision if selecting another product affects rebate guarantees or triggers other financial consequences.
My recommendation is to avoid private label arrangements tied to the PBM and preserve purchasing flexibility. Private labeling alone does not make a medicine clinically inferior or prove that it costs more. The concern is whether the organization recommending the product benefits from that selection in ways the employer cannot evaluate. Require disclosure of affiliated interests and a comparison against competing biosimilars before accepting the recommendation.
HR leaders and brokers can make these expectations part of the purchasing process. Ask for the plan and employee costs of each clinically appropriate alternative. Confirm the financial consequences of choosing a different product. Require support for patients during transitions and preserve clinically appropriate exceptions. After implementation track employee spending and prescription abandonment alongside plan costs.
The next time a biosimilar discussion turns to rebates bring it back to what the employer and employee actually pay. In the illustration above the plan saves $28 while the employee takes on another $708. That tradeoff deserves more scrutiny than a favorable line on a rebate report. An employer’s biosimilar strategy succeeds when the savings help employees afford their treatment.
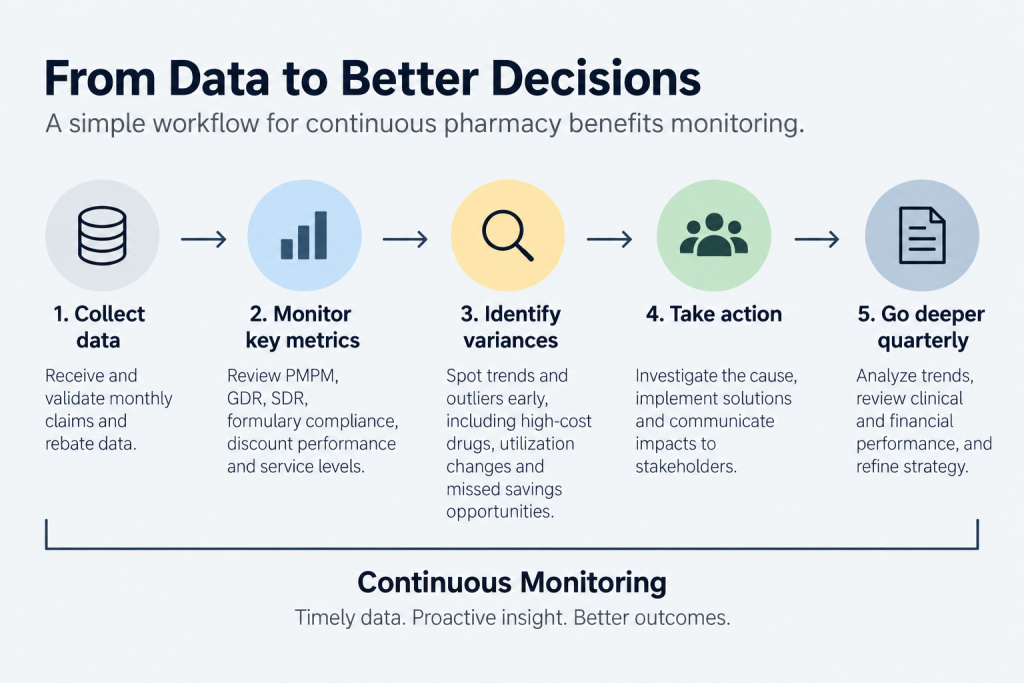
If a pharmacy benefit problem can materially affect spend in one month, waiting three months to review performance is already too late. A pharmacy benefits strategy does not end when the contract is signed, the formulary is selected or the savings projection is approved. That is when oversight begins, because without continuous monitoring in pharmacy benefits management , a plan can drift far from the financial and clinical results the employer expected before anyone notices.
Continuous monitoring is often referred to as ongoing monitoring, but I prefer the word continuous. Ongoing suggests something that happens regularly. Continuous suggests something more active, more deliberate and more urgent. In pharmacy benefits, where one claim, one drug or one missed decision can materially change plan performance, that distinction matters. Monitoring should not simply occur from time to time. It should be built into the way the benefit is managed.
A recent LinkedIn case study makes the point. A pharmacy benefits firm projected that it could reduce a client’s pharmacy spend by more than half. Eight months later, spending was essentially flat. The generic dispensing rate was on target and other management strategies were performing, but one medication, filled 19 times, represented 68% of the plan’s pharmacy spend. An international sourcing program had been identified during renewal as a way to lower the cost, but the employer did not elect it.
The lesson is not simply that employers need to understand which cost saving programs require an opt in. Eight months is far too long to discover that actual results are nowhere near the projection. Once the employer declined the program, the expected financial result changed and the impact should have been communicated immediately. After the first month of claims, the variance should have been visible again, giving the plan sponsor an opportunity to reconsider its decision before additional costs accumulated.
Monthly monitoring should be the standard
Quarterly business reviews have value, but they should not be the first time anyone looks closely at performance. Pharmacy claims move too quickly, and a single high cost prescription can materially change a plan’s results. Every self funded employer should receive a concise monthly performance report showing whether the plan is performing as expected, where results are moving off course and whether corrective action is needed.
The purpose is not another 40 page report. A monthly review should answer a few basic questions: Are we performing as expected? If not, why? Does the plan sponsor need to make a decision? Does anything require action now? Those questions create an early warning system and establish accountability before a manageable problem becomes an expensive one.
If a savings strategy was not implemented, the financial impact should be visible. If specialty spend suddenly increases, the cause should be explained. If generic utilization slips, formulary leakage increases or contractual discounts miss expectations, the issue should not sit unnoticed until renewal. Fiduciary oversight requires more than receiving reports. Plan sponsors and their advisors need information they can use to verify performance and act while there is still time to change the outcome.
What should be monitored every month
The monthly scorecard should include both quantitative and qualitative measures. On the quantitative side, I would expect to see:
PMPM cost
Total cost of pharmacy care (TCoPC)
Discount performance by channel
Generic dispensing rate (GDR)
Specialty dispensing rate (SDR)
Formulary compliance rate
These measures provide a quick view of whether cost, utilization and plan design are working together as intended. PMPM identifies changes in overall pharmacy cost, while discount performance by channel helps expose underperformance that can disappear inside a blended result. GDR, SDR and formulary compliance show whether utilization is moving in the direction the employer intended.
Formulary compliance deserves particular attention. I prefer measuring nonformulary drug spend as a percentage of total net drug spend because a formulary has little financial value if exceptions and workarounds routinely allow higher cost drugs through. My working benchmark is 2% to 3% or less for paid nonformulary spend, with 3% to 5% deserving review and anything above 5% triggering a deeper audit. The goal is not a perfect number. The goal is to know when the formulary stops performing as designed.
Numbers do not tell the whole story
Service performance belongs on the monthly scorecard too. Two measures I would track are time to answer and first call resolution rate. Employers pay pharmacy benefit administrators and PBMs to solve problems, not simply process claims. Long hold times, repeated transfers and unresolved member issues create more work for HR teams while frustrating employees.
First call resolution matters because speed without resolution is meaningless. A call answered in 20 seconds is not impressive if the member has to call three more times. Qualitative monitoring should also surface recurring complaints, escalation themes, prior authorization delays, pharmacy access issues and problems that repeatedly reach the employer’s benefits team.
A strong pharmacy benefit partner should reduce the administrative burden on the employer, not push it back to HR. Service data can expose problems the claims file will never show. Reviewing financial, clinical and service performance together gives the plan sponsor a clearer picture of whether the benefit is working for both the plan and its members.
Quarterly reviews should go much deeper
Monthly monitoring is the dashboard. The quarterly review should go much deeper into what is driving the numbers, including top cost drugs and members, specialty trends, utilization changes, formulary exceptions, prior authorization activity, clinical program performance, discount guarantees, rebate performance and emerging therapies likely to affect future spend. The review should explain what happened, why it happened and what needs to change.
Actual performance should also be compared with the original financial projection, not just contractual guarantees. If the proposal projected a 30% reduction and the plan is tracking at 12%, the conversation should start there. What changed? Which assumptions were wrong? Which programs were not implemented? What can still be corrected? A meaningful quarterly review should answer those questions directly.
Every material variance should end with an owner, an action item and a date. Otherwise, the quarterly review becomes a presentation instead of an oversight process. The value comes from identifying what needs attention, deciding what happens next and assigning responsibility for follow through.
Eight months is too late
Pharmacy benefits are too complex and too expensive to manage by looking backward once or twice a year. Employers should know whether their strategy is working while there is still time to do something about it. Monthly monitoring catches problems early, while quarterly reviews provide the deeper analysis needed to correct course.
The case study is a useful reminder of what happens when monitoring comes too late. One medication accounted for 68% of spend, the expected savings never materialized and eight months passed before the financial impact was fully understood. The issue was not simply the drug or the program the employer declined. The larger failure was allowing the variance to persist without timely intervention.
For plan sponsors operating under a fiduciary standard of care, projected savings are not enough. Performance must be measured, material changes must be communicated and corrective action must follow when results fall short. Continuous monitoring is how employers move pharmacy benefits oversight from periodic reporting to documented accountability.
Pharmacy benefits procurement and oversight platforms promise to make a difficult job easier. They collect PBM proposals and compare pricing. They also model savings and produce reports that brokers can present to employers. The technology saves time but it can create a false sense of certainty.
A report may show that one PBM will save an employer millions of dollars. Yet the results often rely on different assumptions and contract definitions. They may also apply different financial standards. That is not an apples to apples comparison.
A Polished Report Does Not Guarantee a Fair Comparison
Every PBM has its own way of defining the financial terms in its proposal. One may classify brand drugs based on its own list. Another may use a third party database. A third may reserve the right to change classifications during the contract term.
Each proposal may include a retail brand guarantee. Yet those guarantees may not cover the same drugs. The same issue applies to rebates because PBMs can define eligible claims differently.
Contract definitions determine which claims count toward a guarantee. They also control exclusions and how performance is reconciled. If those definitions are not standardized then the platform may reward the PBM with the most favorable assumptions. The math can be correct while the conclusion is wrong.
A PBM Can Decline Key Requests and Still Win
I recently had a candid conversation with a former CFO of one of the three largest PBMs. We discussed how large PBMs respond to requests from brokers and consultants. The former CFO told me that the PBM could decline about 20% of the requests in an RFP and still win the business.
That statement has stayed with me. Employers assume the selected PBM earned the business by providing the strongest proposal. In practice the PBM may reject important protections and still finish first because its modeled savings look attractive.
A PBM might decline stronger audit rights or reporting requirements. It might reject clear pricing terms or data access provisions. Those exceptions may receive little attention if the financial model still ranks the PBM first.
Many scoring systems place too much weight on projected savings. They place too little weight on whether those savings are enforceable after implementation.
The Service Agreement Is Reviewed Too Late
On another occasion I participated in a webinar presented by one of the major pharmacy benefits procurement platforms. I asked when the PBM service agreement was incorporated into the evaluation.
The presenter said it would be reviewed after the field had been narrowed to the top three finalists. That answer revealed a serious flaw. The platform could eliminate bidders before reviewing the document that controls the arrangement.
The service agreement determines whether the pricing proposal is enforceable. It contains the definitions and exclusions that affect the employer’s actual cost. It also establishes audit rights and access to data.
A rebate guarantee means less if the PBM controls which claims qualify. An aggressive discount means less if the PBM can change drug classifications. The proposed economics cannot be separated from the contract language that governs them.
The Biggest Cost Drivers Receive Too Little Weight
The biggest failure of many platforms is their limited consideration of clinical program management. Their evaluations tend to focus on price, including discounts and rebates. Those measures matter but they do not show how well a PBM will manage the medications used by the plan.
Formulary and utilization management are two important examples. Formulary management determines which drugs are covered and how they are positioned against available alternatives. The benefit design determines what members pay. That cost sharing is often reflected through formulary tier placement.
Utilization management applies tools such as prior authorization and step therapy to influence when and how medications are used. Depending on the plan, formulary and utilization management decisions can influence as much as two thirds of pharmacy costs.
A PBM can offer aggressive pricing guarantees while doing little to manage either cost driver. The employer may receive a strong discount on a high cost drug that should not have been preferred or used in the first place. That is not effective clinical program management.
Generic Conversion Savings Rate measures the savings achieved when eligible brand drug use moves to lower cost generic alternatives. Poor performance should not be dismissed as the unavoidable result of physician prescribing. The PBM’s formulary and utilization management programs can influence whether those conversions occur.
The financial interests of PBM owned pharmacies may also affect the outcome. In certain CVS arrangements I have reviewed, its retail pharmacies receive a higher dispensing fee for a brand drug than for a generic drug. The basic work required to dispense the prescription does not change because the drug is branded. Yet the reimbursement can reward the pharmacy more for dispensing the higher cost product.
This matters because the PBM owns the pharmacy. A platform that compares only discounts and dispensing fees may miss the incentive created by that ownership. The Federal Trade Commission has also reported that the three largest PBMs reimbursed their affiliated pharmacies at higher rates than unaffiliated pharmacies for nearly every specialty generic drug it examined.
A proper evaluation should examine formulary design and generic conversion. It should also review prior authorization and step therapy programs. Without that analysis the platform measures drug prices but not how well the PBM manages cost.
Oversight Requires More Than a Dashboard
Oversight platforms can display claims trends and rebate payments. They can also report pricing performance and guarantee results. Those dashboards are useful only when the data is complete and the measurements match the agreement.
A dashboard may report that a PBM met its discount guarantee. That means little if claims were excluded incorrectly or drug classifications changed. It also means little if poor clinical management continues to drive unnecessary spending.
True oversight requires tracing performance back to claim level data and contract language. It also requires examining prescribing patterns and the financial incentives behind formulary and pharmacy decisions.
Employers Need a Fiduciary Procurement Standard
Pharmacy benefits procurement should apply one financial and contractual standard to every bidder. The people conducting the evaluation must also be prudent experts who understand PBM pricing and contracting.
At a minimum each PBM should be evaluated using:
The same claims data and utilization period
The same trend assumptions
The same drug classifications
Standardized contract definitions
Consistent treatment of fees and rebates
Service agreement terms from the beginning
Evaluation of clinical program management including formulary and utilization management
Meaningful scoring consequences for contract exceptions
Clear separation of guaranteed savings from projected opportunities
Independent review by a qualified pharmacy benefits expert
Expert review should test more than the calculations. It should determine whether pricing terms are enforceable and whether the results account for the PBM’s financial incentives. A platform can produce an answer. A prudent expert must determine whether the assumptions and contract terms can be trusted. That judgment is central to a fiduciary standard of care.
A PBM profit and loss statement, or PBM P&L, can report billions in revenue and still show a thin profit margin under generally accepted accounting principles. That margin may reveal little about how much the PBM earns from an employer’s prescription drug program.
For brokers, consultants, HR leaders and CFOs, the better question is not simply, “What is the PBM’s margin?” Ask which dollars were counted as revenue, passed through or retained as compensation.
Why PBM revenue can be misleading
PBMs sit between plan sponsors, pharmacies, drug manufacturers and members. Large sums move through that position. A PBM may receive money from a plan sponsor to reimburse pharmacies. It may also collect manufacturer rebates before sending an agreed portion to the plan.
Those pass-through amounts can make reported revenue look enormous even when the PBM does not keep the money. The accounting treatment matters because profit margin uses revenue as its denominator.
Net profit margin = net income ÷ reported revenue × 100
The USC Schaeffer Center white paper shows that principal and agent accounting can produce the same net income with sharply different margins. The principal approach includes certain pass-through payments as revenue and expense. The agent approach excludes them and reports the PBM’s retained compensation as revenue.
FASB Topic 606 guidance focuses on whether a company controls a promised good or service before it reaches the customer. A company may be the principal for one service and the agent for another. The contract and service therefore matter more than a companywide label.
The revenue sources employers should identify
A useful PBM P&L should separate each way the company earns money. Common sources include claims processing and administrative fees, pharmacy spread, retained rebates, rebate administration fees, manufacturer service or data fees, clinical program fees and implementation fees.
Vertical integration adds another layer. Profit may be earned by an affiliated specialty pharmacy, mail-order pharmacy, rebate aggregator or group purchasing organization. The FTC’s January 2025 staff report found substantial income tied to specialty generic drugs across the three largest PBMs and their affiliated pharmacies. A consolidated segment can conceal which affiliate earned the profit.
Two formulas help expose important compensation:
Pharmacy spread = amount billed to the plan and member − amount paid to the dispensing pharmacy
Retained rebate = rebates collected − rebates credited or paid to the plan
Consider one prescription. The plan and member pay $400. The PBM pays the pharmacy $360, leaving $40 of spread. The manufacturer pays a $50 rebate and the plan receives $45, leaving $5. Add a $2 processing fee and net retained compensation is $47 before operating expenses. Gross revenue could be $452 even though the PBM keeps $47.
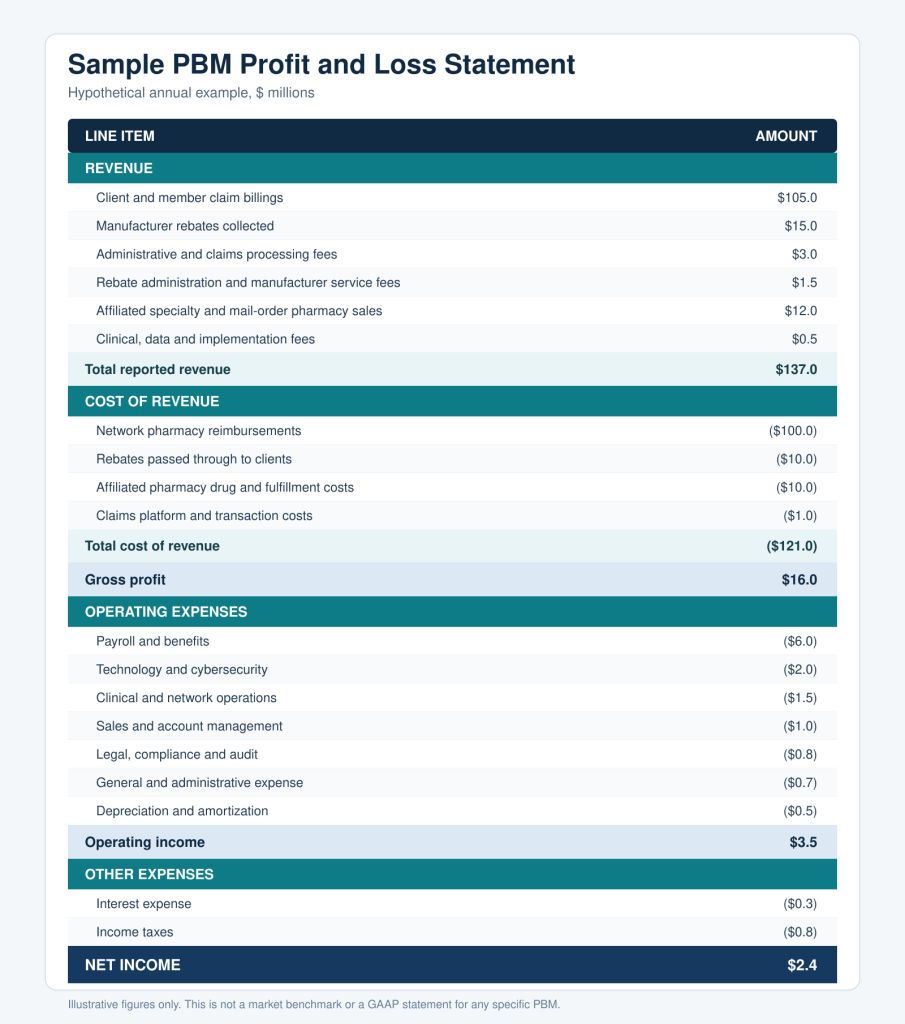
A sample PBM P&L Statement
The following annual example is hypothetical and stated in millions. It is not a market benchmark. It shows a gross presentation so pass-through cash can be seen.
The reported net margin is 1.8 percent, calculated as $2.4 million divided by $137 million. That looks modest. Yet net retained compensation is $17 million after subtracting pharmacy reimbursement, rebate pass-through and affiliated pharmacy product costs. Net income divided by net retained compensation is 14.1 percent.
The second calculation is a management view rather than a substitute for GAAP. Its value is diagnostic. It shows why employers should not accept a headline margin as proof that compensation is reasonable.
What a plan sponsor should request
A plan sponsor should request three files for each reporting period:
A claim-level paid claims file showing the amount billed to the plan and member, the amount paid to the pharmacy and all adjustments.
A rebate remittance file showing gross rebates and fees received, amounts credited to the plan and payment dates.
A compensation and affiliate schedule identifying each direct and indirect payment, recipient, related entity and shared expense allocation.
Reconcile these files to the PBM P&L and require audit rights covering subcontractors and affiliates. An “administrative fees” line is incomplete if the PBM also earns money through pricing differences or an affiliated pharmacy.
The purpose is to understand the arrangement’s economics. A fiduciary standard of care requires the employer and its advisers to identify all compensation, judge whether it is reasonable and confirm that the contract serves the plan and its members.
Employers often rely on brokers and consultants to evaluate PBMs on their behalf. In some cases the PBM under consideration may also have a financial relationship with the advisor. H.R. 7895 is intended to address that conflict through a proposed PBM kickback ban and bring greater transparency to the selection process.
The PBM Kickback Prohibition Act would not prohibit every business relationship between a PBM and a broker. It would restrict payments tied directly or indirectly to referrals, recommendations, RFP access, market checks, contract renewals or the value of plan business. The principle is straightforward: compensation should not influence which PBM an advisor recommends to an employer.
As of July 2, 2026 the bill has been reported by the House Education and Workforce Committee. It has not passed the House and is not law. Even so it gives employers, brokers and PBMs a clear view of where lawmakers believe stronger protections may be needed.
What the Bill Would Prohibit
The legislation would amend ERISA rules governing service provider arrangements. A PBM could not pay direct or indirect compensation to a person or entity for activities connected to winning or keeping plan business. The restriction would focus on the purpose of the payment rather than the label placed on it.
The proposed restriction would apply to compensation tied to:
Referring or recommending a PBM
Placing, retaining or renewing a PBM
Designing or participating in an RFP
Conducting market checks or evaluations
Providing access to employer plan business
Payments based on the volume or value of business
A PBM could not avoid the rule by describing compensation as a consulting fee, marketing allowance, technology fee, sponsorship or administrative payment. If the payment was connected to the employer’s PBM decision it could still be prohibited. The bill is written to examine the substance of the arrangement rather than the name used in the contract.
Payments from a PBM to a broker, consultant or related company would generally be presumed prohibited unless the parties maintained written documentation showing that the payment reflected fair market value for legitimate services. They would also need to show that the payment was not connected to the employer’s PBM selection. That presumption places the burden on the PBM and advisor to demonstrate that the arrangement was proper.
What It Means for Self-Funded Employers
For employers the main benefit is a more transparent PBM selection process. Brokers and consultants would have less incentive to favor a vendor because of compensation received from that vendor. Employers would also have a clearer basis for evaluating whether the recommendation was made in the best interest of the plan.
The bill also reinforces the importance of fiduciary oversight. Employers need to understand who is being paid, how much they are being paid and whether the compensation could affect the advice they receive. That review should extend to payments involving affiliates and other companies connected to the PBM or advisor.
A prohibited payment could create more than a disclosure problem. It could affect whether the PBM contract qualifies for an exemption from ERISA’s prohibited transaction rules. That may create exposure for the plan and the people responsible for approving the arrangement.
Employers may need to:
Require disclosure of payments involving the PBM, broker and their affiliates
Obtain written certification that no prohibited compensation is being paid
Add audit, termination and indemnification protections to PBM contracts
Review how the broker or consultant is compensated
Document why the selected PBM is in the best interest of the plan
Some advisory costs may become more visible under this model. A broker that previously received compensation from a PBM may begin charging the employer directly. That does not automatically mean the employer is paying more because the cost may already have been embedded elsewhere in the arrangement.
What It Means for Non-Fiduciary PBMs
The bill could create a meaningful change for PBMs that use broker compensation to gain access to employer business. Payments tied to placement, renewals, preferred vendor status, market checks or RFP participation would become difficult to defend. PBMs that rely heavily on these arrangements may need to rethink how they compete for business.
The legislation reaches beyond traditional commissions. It could also affect payments made through affiliates or arrangements described as data services, consulting, technology support or marketing. A payment routed through another company would not necessarily fall outside the proposed restriction.
PBMs would likely need to examine:
Referral fees
Placement and renewal bonuses
Preferred vendor arrangements
Conference sponsorships
Technology and data service payments
Payments to broker owned or affiliated entities
The bill would not require a PBM to become a fiduciary. It would also leave several PBM revenue sources untouched including spread pricing, retained rebates, formulary payments, specialty pharmacy margins and revenue earned through affiliated companies. Employers should not view the bill as a complete answer to PBM conflicts because it addresses only one part of the procurement process.
What It Means for Fiduciary PBMs
The bill would not create a special exemption for fiduciary PBMs. A PBM that accepts fiduciary responsibility would still be prohibited from paying for referrals, placement or retention. Fiduciary status would not excuse a compensation arrangement that violates the proposed rule.
A fiduciary PBM that relies on disclosed administrative fees and does not compensate brokers for access to plan business should face less disruption. Its main responsibility would be documenting its practices and confirming that no affiliate or business partner is making prohibited payments on its behalf. Clear contract language and written certifications would become even more important.
The legislation may also improve the competitive position of fiduciary PBMs. A market that limits payments tied to placement gives employers more room to evaluate cost, service, clinical performance and contract terms. PBMs should earn business by delivering measurable value and honoring a clear duty to the plan rather than paying for influence over the recommendation.
Fiduciary status should still be verified rather than accepted as a marketing claim. Employers should confirm that the PBM accepts the obligation in writing and that its revenue model supports the promise being made. A fiduciary standard of care has value only when it is reflected in the contract and the compensation structure.
What It Means for Brokers and Consultants
Many brokers already disclose their compensation and put their clients’ interests ahead of vendor relationships. The legislation is more likely to strengthen those firms than disrupt them. Brokers operating under clear compensation models may have an easier time demonstrating that their advice is independent.
The bill is aimed at compensation arrangements that could influence PBM recommendations, evaluations, renewals or contract placement. It should not be read as an indictment of the broker community. The focus is the financial arrangement between the advisor and the PBM rather than the profession itself.
Legitimate work performed for a PBM may still be allowed. The PBM and broker would need records showing what services were performed, why the payment reflected fair market value and why the arrangement had no connection to employer plan business. That standard may become difficult to meet when the same firm is advising employers on which PBM to select.
A direct and fully disclosed compensation model gives employers and brokers a clearer basis for trust. It makes the broker’s role easier to understand and reduces questions about whether vendor payments influenced the recommendation. Brokers that already operate this way should be well positioned if the bill becomes law.
The Bill Has Limits
H.R. 7895 focuses on payments made by PBMs. It does not apply the same restrictions to medical carriers, third party administrators or every other health plan vendor. Similar compensation practices could therefore continue elsewhere in the benefits market.
Employers should examine all vendor relationships rather than assuming that PBM compensation is the only source of potential conflict. The bill also does not replace an employer’s fiduciary process. Plan sponsors must still compare total cost, contract terms, clinical outcomes, data access and all sources of vendor revenue.
The broader message is difficult to ignore. Employers should know who is paying their advisors and whether those payments could influence the advice they receive. The goal is not to blame brokers but to protect the integrity of the procurement process and keep the plan’s interests at the center of the decision.
I read a LinkedIn post a few days where a broker said he was cold called by a PBM offering a 10% commission payable to the consultant. Around the same time, I was still seeing RFPs asking for lump monthly compensation to be paid from the PBM to the consultant.
Both examples point to the same problem. The industry has placed new expectations on PBM disclosure and transparency, but old compensation practices are still showing up in new proposals. If transparency is going to mean anything, it has to apply across the entire pharmacy benefit ecosystem, including how brokers, consultants, TPAs, and PBMs are paid.
A no-nonsense pharmacy benefit model is not complicated. It starts with a simple idea. The plan sponsor should know where the money goes, who gets paid, why they get paid, and whether those payments align with the best interests of the plan and its members.
The point should sound obvious. In pharmacy benefits, too often it does not reflect how the business works. Too many PBM arrangements still depend on money moving through side doors, including rebates, spread pricing, network differentials, data fees, consultant payments, broker payments, “clinical” programs tied to drug spend, and contract terms only a lawyer could enjoy.
A no-nonsense model strips all of it down. It puts the plan sponsor back in control, makes the economics visible, and forces every stakeholder to answer a basic question. Does this arrangement serve the plan, the members, and the fiduciary standard of care?
Clean PBM Economics
The PBM should not profit from the plan unless the profit is fully disclosed. Preferably, the PBM should earn its revenue through a clearly stated administrative fee. The client sees the fee, understands the fee, and can compare the fee against the work being performed.
A clean fee structure creates better alignment. When a PBM earns revenue in other ways, the incentives get messy fast. If money is tied to rebates, the PBM may benefit when high-cost drugs are used. If money is tied to ingredient cost spreads, the PBM may benefit when the plan pays more than it should. If money comes from sources the client cannot see, the client cannot determine whether the PBM is managing the benefit or monetizing it.
A fiduciary pharmacy benefits administrator should not need hidden economics to be successful. It should be paid for administration, clinical management, service, reporting, implementation, and accountability. The economics should be visible, documented, and easy for the client to verify.
No Unnecessary Cash Outflows
A no-nonsense model also means no unnecessary outflow of plan sponsor cash. Reasonable implementation fees can make sense when real work is involved. A PBM transition requires eligibility setup, benefit configuration, formulary review, clinical program buildout, accumulator coordination, member communications, testing, and go-live support.
Ongoing monthly payments to brokers or consultants from the PBM should not be part of the model. Those payments create questions the client should not have to ask. Who is the consultant working for? Is the recommendation based on the client’s best interest or on a revenue arrangement behind the scenes?
If a broker or consultant provides value, the client should pay them directly. Doing so keeps the relationship clean. It also protects the consultant’s credibility because the advice is no longer connected to an undisclosed or indirect payment stream from the vendor being recommended.
The industry needs to be honest with itself. PBMs are being asked to disclose more, pass through more, and operate with cleaner economics. Fair enough. Brokers, consultants, TPAs, and advisors also have to adjust. If transparency is the standard, compensation arrangements tied to PBM selection should not be buried in RFP terms, side agreements, or monthly payment schedules routed through the vendor.
The same standard applies to pharmacy management services and other add-on arrangements. If a service is needed, define it, price it, disclose it, and measure it. Do not bury it in the PBM’s economics and pretend it is free. Nothing in pharmacy benefits is free. Someone pays, and most of the time, it is the employer.
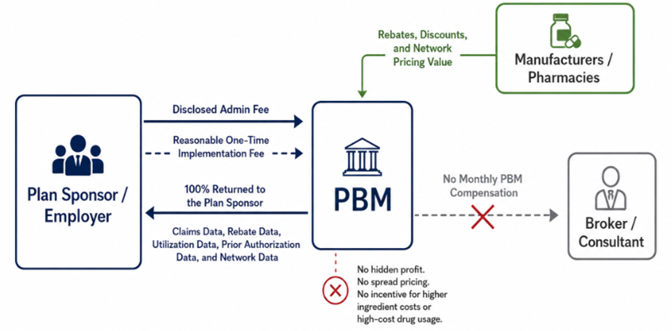
A Clean Pharmacy Benefit Flow
Client-Owned Data
A no-nonsense model also means the client owns its data. Not summaries. Not dashboards controlled by the vendor. Not reports filtered through someone else’s business interests. The client should own its claims data, rebate data, utilization data, eligibility data, prior authorization data, and pharmacy network data.
Data ownership matters because pharmacy benefit decisions cannot be managed on trust alone. Employers need the ability to verify pricing, monitor trends, evaluate clinical programs, review member disruption, test performance guarantees, and confirm whether contract terms are being followed.
If the client cannot access its own data, the client is not really in control of the plan. A vendor may say all the right things in sales meetings, but without data access, the plan sponsor has no practical way to confirm what is happening behind the scenes.
Full Audit Rights
Full audit rights are part of the same standard. A plan sponsor should have the right to audit claims, pricing, rebates, fees, guarantees, and any other financial arrangement tied to the pharmacy benefit. The audit should not be limited by narrow contract language, unnecessary delays, or vendor-controlled definitions of what can be reviewed.
A fiduciary standard of care requires more than a promise. It requires evidence. Audit rights give the plan sponsor a way to test whether the PBM’s conduct matches the contract and whether the contract matches the employer’s expectations.
In a no-nonsense model, audit rights are not treated as a threat. They are part of good governance. If the PBM is doing what it says it is doing, audit rights should not be a problem.
The Standard Employers Should Expect
In my view, a no-nonsense pharmacy benefit model comes down to a few basic principles.
The PBM gets paid in a clear and disclosed way.
The plan sponsor receives all rebates, discounts, and pricing value intended for the plan.
The PBM does not earn more when drug costs go up.
The broker or consultant is not quietly paid by the PBM.
The client owns the data.
The client has full audit rights.
The contract supports the fiduciary standard of care instead of working around it.
Employers are not asking for anything radical. They are asking for pharmacy benefits to work the way vendor relationships should have worked all along. They need clean economics, clear contracts, useful data, and a PBM willing to be measured by the same standard it claims to represent.
A no-nonsense pharmacy benefit model means fewer games, fewer excuses, and fewer hidden incentives. More importantly, it means every stakeholder has to live under the same standard they are asking others to meet.
The two primary goals of a pharmacy benefit manager or pharmacy benefit administrator are simple: contain cost and improve outcomes. Outcomes must include safety. If a pharmacy program saves money while exposing members to avoidable risk, it is not well managed. If it improves access but ignores waste, duplicate therapy, poor adherence, inflated drug selection, or unsafe utilization, it is not well managed either.
Cost containment and outcomes have to move together. One without the other creates problems for the plan, the member, and the employer. Many pharmacy programs go off track at this point. The basic goals are easy to state, but vendors often make the process feel more complicated than necessary. Complexity becomes a shield. It keeps employers from asking direct questions and makes ordinary oversight feel like specialized work only insiders can understand.
Pharmacy benefits are technical, but the management framework is not complicated. The job is to set clear standards, follow them, measure results, and hold the people managing the program responsible for performance. Most problems begin when expectations are unclear, hidden, ignored, or changed without the plan sponsor understanding the financial impact.
Once a plan sponsor loses visibility into how drugs are selected, approved, dispensed, and monitored, the program becomes harder to govern. Costs rise, exceptions multiply, and HR is left trying to explain decisions to employees without having full control over the process behind those decisions. This creates frustration for members and risk for the employer.
Managing pharmacy benefits does not require making the program more complex. It requires discipline. The plan needs clear goals, sound clinical standards, defined financial expectations, and useful reporting. Without those basics, even the best-looking PBM arrangement can drift away from the employer’s interests.
Start With Appropriate Drug Selection
Once the goals are clear, the work begins with a basic question: was the appropriate medication selected for the patient? The medication should be clinically appropriate, safe, effective, and cost-conscious. It should fit the patient’s diagnosis, history, prior therapy, risk factors, and benefit design. It should also make financial sense for the plan when lower cost therapies can reasonably produce the same or better outcome.
This is where formulary management, prior authorization, step therapy, quantity limits, clinical edits, specialty drug review, and medication policy come into play. These tools are often described in a way that makes them sound cold or restrictive. Poorly designed, they can be. Properly managed, they protect the patient and the plan. Prior authorization should not exist to create friction for the sake of denying care. It should confirm the drug is being used for the right patient, for the right condition, at the right dose, and at the right point in therapy.
Step therapy should not be a game of delay. It should help determine whether a clinically sound, lower-cost option should be tried before moving to a higher-cost therapy. Quantity limits should not be arbitrary. They should reflect safe dosing, FDA labeling, clinical evidence, and common-sense utilization control. Medication policies should not sit in the background where no employer ever sees them. They are the operating standards behind many pharmacy decisions.
Employers do not need to become pharmacists, but they do need to understand how these standards are built, who approves them, how often they are reviewed, and whether they align with the plan’s goals. When drug selection is handled correctly, pharmacy benefits become much easier to manage. When it is handled poorly, everything downstream gets more expensive.
Drug Selection Is a Governance Issue
Many employers focus too much on discounts, rebates, and guarantees while giving too little attention to drug selection. This has it backwards. A large rebate on the wrong drug is not a win. A low ingredient cost on a medication the patient does not need is not a win. A broad formulary with weak clinical controls may feel member-friendly until the plan sees the claims experience. The real question is not whether the PBM claims to manage trend. The real question is whether the PBM can explain, defend, and document how drugs are selected and monitored.
Why was the medication approved?
Was a lower-cost option available?
Was the member previously treated with an alternative?
Was the dose appropriate?
Was the prescription filled through the right pharmacy channel?
Was the drug medically necessary?
Was there waste, duplication, or a safety concern?
If those questions cannot be answered clearly, the employer does not have a pharmacy strategy. It has a vendor relationship. Drug selection drives more than the pharmacy claim. It affects member experience, medical claims, adherence, safety, employee trust, and the employer’s ability to manage plan assets.
When plan sponsors treat drug selection as a vendor-only function, they give up control over one of the most important cost and quality levers in the health plan. Good governance does not mean the employer makes clinical decisions. It means the employer understands the standards, reviews the results, and holds the administrator responsible for applying them consistently. Fiduciary oversight becomes practical here. It is not about micromanaging clinical judgment. It is about making sure decisions are made in the best interest of the plan and its members, not around hidden economics or vendor convenience.
Make Sure the Patient Takes the Medication
Selecting the appropriate medication is only part of the job. The patient also has to take it. This is where many plans lose money and outcomes suffer. A drug can be properly selected, properly approved, and reasonably priced. None of it matters if the patient does not take it as prescribed.
Medication adherence is especially important in chronic conditions such as diabetes, high blood pressure, high cholesterol, asthma, depression, and other long-term conditions. Poor adherence can lead to avoidable medical claims, emergency room visits, hospitalizations, disease progression, and lower quality of life. Every employer paying medical and pharmacy claims should care about whether members are taking the medications intended to keep them stable because adherence affects total cost and workforce health.
Adherence can be supported through refill reminders, pharmacist outreach, medication therapy management, synchronized refills, 90-day supplies where appropriate, member education, lower-cost alternatives, and benefit designs that remove unnecessary barriers for high-value drugs. It can also be hurt by poor communication, confusing coverage requirements, unaffordable copays, pharmacy disruption, unnecessary prior authorization delays, and designs built around vendor economics instead of patient behavior.
The issue is not simply whether the member filled the drug. The better question is whether the member is likely taking it consistently enough to receive the intended clinical benefit. A paid claim shows access. It does not always show follow-through. A pharmacy program should be measured not only by whether drugs were dispensed, but by whether members stay on the therapies that protect their health and reduce avoidable costs.
Measure What Matters
Employers do not need a dashboard with 200 metrics. They need a smaller set of measures tied directly to cost containment, outcomes, safety, and member experience. The point is not to bury HR, finance, or the benefits team in reports. The point is to make the program manageable and help the employer make better decisions.
For drug selection, the employer should know whether members are using clinically appropriate, cost-effective therapies. Measures such as generic dispensing, specialty utilization, formulary compliance, prior authorization outcomes, appeals, and high cost claim review help show whether the plan is controlling waste without creating unnecessary barriers to care.
For adherence, the employer should understand whether members with chronic conditions are staying on therapy. Proportion of days covered, often called PDC, is a practical measure. A common threshold is 80% adherence, meaning the member had the medication available for at least 80% of the measurement period. Missed therapy often shows up later as higher medical costs, lower productivity, and worse member outcomes.
For safety and financial management, the employer should expect reporting on duplicate therapy, high risk medications, opioid utilization, dose concerns, total cost of care, rebates, member cost share, specialty trend, and plan paid amounts. Good reporting should tell the employer what happened, why it happened, what is being done about it, and whether the action worked.
A lot of vendor reporting falls short here. It may look polished, but it does not always help the employer govern the program. A useful report should create clarity. It should make the employer smarter, not more dependent on the vendor for interpretation.
Do Not Let Complexity Replace Accountability
Pharmacy benefits become complicated when employers allow vendors to set the standards, control the data, interpret the results, and define success on their own terms. Once this happens, the employer stops managing the benefit and starts reacting to the vendor’s version of the story.
Employers do not need a more complicated program. They need a simpler management framework with accountability built into it. Define the goals. Set the standards. Select appropriate therapies. Make sure patients take their medications. Measure cost, outcomes, safety, and member experience. Review exceptions. Hold vendors accountable. Repeat the process.
The details matter, but the framework is straightforward. Employers, brokers, and pharmacy benefit consultants do not need to accept confusion as the price of admission. Pharmacy benefits should not be a black box. They should be governed like any other major plan asset, with clear standards, clear data, and clear accountability.
When employees do not understand why a drug was denied, changed, or delayed, HR owns the frustration even when the vendor made the decision. Pharmacy benefit governance cannot be treated as a back-office function. It affects employee trust, benefit satisfaction, and the employer’s credibility.
Managing pharmacy benefits is not easy, but it is simpler when the plan sponsor refuses to let the program drift away from its core purpose: contain cost, improve outcomes, protect the patient, and protect the plan. Vendors may benefit when the program feels too complicated to challenge. Employers do not.
Once the basics are nailed down, employers and their consultants can move to more advanced strategies, including disease management programs, targeted clinical interventions, and other initiatives designed to improve outcomes. But those efforts work best when the foundation is already in place. Pharmacy benefits do not need more mystery. They need standards, measurement, transparency, and accountability.
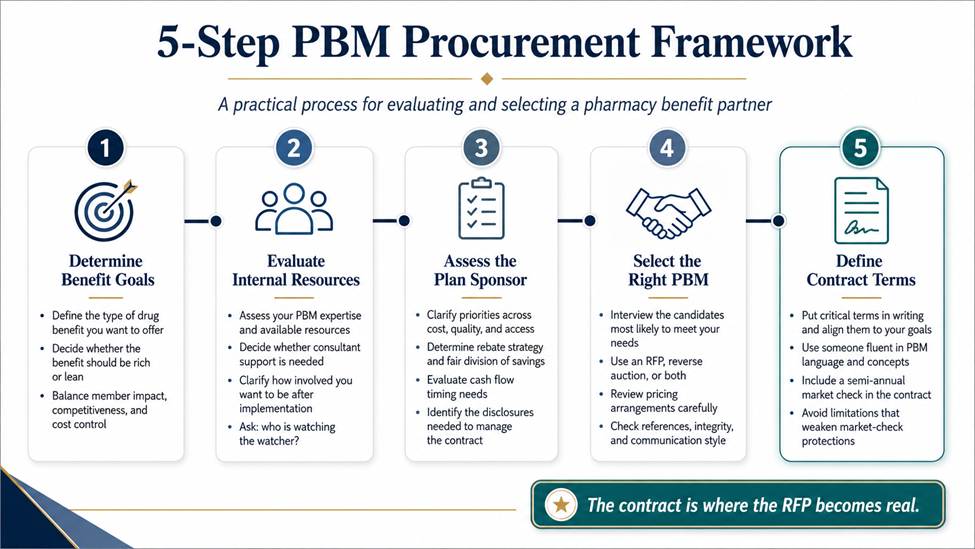
The RFP does not select the PBM. The contract does.
A recent RFP reminded me why pharmacy benefit procurement cannot be judged by spreadsheet pricing alone. After we submitted our proposal, we learned that some competing bidders were quoting brand retail 30 days discounts as high as 33% off AWP. At first glance, that may look attractive. But those discounts are well below WAC and would leave most pharmacies underwater on brand claims. The bigger issue was how the numbers were built.
Even though the RFP instructed bidders not to include embedded discounts, some appeared to fold other financial credits into the brand discount, making the headline number look stronger than the actual pharmacy reimbursement economics could support. In this context, an embedded discount means a credit, offset, rebate value, access fee, or other financial concession included inside a quoted discount instead of being disclosed as a separate line item. Employers, brokers, and consultants cannot rely on headline discounts. They must know what is included, what is excluded, and whether the pricing can actually work at the pharmacy counter. To the consultant’s credit, the following RFP was revised to prevent bidders from repeating the same tactic.
The first trap with PBM RFPs is that too many of them reward the best-looking spreadsheet, not the best deal. A bidder can make a proposal look aggressive by quoting eye-catching discounts, rebate guarantees, and low administrative fees. The employer sees a clean side-by-side comparison and assumes the lowest projected net cost is the winner. I have seen this mistake enough times to know better. A spreadsheet can compare numbers, but it cannot tell you whether those numbers are enforceable, whether the definitions are tight, or whether the bidder has left itself room to soften the offer once the contract is signed.
This is where many RFPs go sideways. They score proposals as if every bidder used the same assumptions and pricing logic. In pharmacy benefits, that is a dangerous assumption. A brand discount can be watered down by drug reclassification. A rebate guarantee can shrink once exclusions are applied. A low admin fee can become much less impressive if other revenue streams sit outside the pricing exhibit. The issue is not that spreadsheets are useless. They are necessary. But they should start the diligence process, not end it.
The second trap is that many RFPs give bidders too much room to maneuver. That sounds like a small process issue, but it can change the outcome. If the RFP says not to include embedded discounts, then the response should not include embedded discounts. If the RFP asks for pass-through pricing, the bidder should explain what is passed through, when it is passed through, and how the employer can verify it. If the RFP asks for a rebate guarantee, the bidder should not be allowed to hide behind broad language, selective exclusions, or definitions that only become clear after finalist selection.
This is where a good consultant earns their fee. The RFP has to force every bidder onto the same playing field. Not roughly the same. The same. That means the pricing assumptions need to be certified. Exclusions need to be disclosed plainly. Definitions need to be nailed down before scoring, not negotiated after the winner is chosen. If a bidder includes credits, access fees, purchasing economics, manufacturer revenue, or any other pricing input that was not requested, they should have to identify it and show how it affects the projected cost. If they do not comply, the response should be adjusted, challenged, or disqualified. Otherwise, the process rewards the bidder willing to bend the rules and penalizes the bidder who followed them.
The third trap is that many PBM RFPs stop at vendor selection instead of building accountability after implementation. This is one of the most common failures I see. A proposal may include strong pricing guarantees, clean disruption reports, and polished service commitments, but the employer still needs a way to verify performance once claims start processing. Without claim-level reporting, audit access, rebate reconciliation detail, service guarantees, implementation milestones, and real consequences for missed commitments, the employer is relying on trust where oversight is required.
That is where fiduciary procurement separates itself from ordinary procurement. The goal is not just to pick a PBM or pharmacy benefit administrator. The goal is to create a structure for monitoring the plan after the award is made. Did the network perform as represented? Were rebates collected and passed through according to the agreed terms? Were claims adjudicated using the promised pricing? Were exclusions applied properly? Were members disrupted beyond what the proposal suggested? These are not academic questions. They are the questions that determine whether the employer got the deal it thought it bought.
Drafting, negotiating, and finalizing a contract with a PBM are the three most important tasks during an RFP. The proposal may get a bidder to the table, but the contract determines whether the employer can enforce what was promised. Too many plan sponsors treat contracting as an administrative step after vendor selection. That is backwards. The contract is where the RFP becomes real. If the pricing, definitions, guarantees, audit rights, reporting obligations, and fiduciary expectations do not make it into the contract, they are little more than sales language.
The strongest RFPs force bidders to prove three things. The pricing must be verifiable. The contract must be enforceable. The model must be accountable after go-live. That requires clear attestations, tight definitions, full disclosure of exclusions, audit rights, reconciliation rules, service guarantees, and consequences for non-compliant responses. More importantly, it requires a mindset shift. The RFP is not just a purchasing document. It is the first draft of the oversight framework.
My view is simple. If a PBM’s offer depends on vague definitions, selective exclusions, nonstandard pricing inputs, or assumptions that cannot be explained plainly, that is not a strong bid. It is a warning sign. A fiduciary procurement process does not chase the lowest bid. It selects the most verifiable, enforceable, and accountable bid. That is the difference between buying a spreadsheet and overseeing a pharmacy benefit plan.
We use cookies to ensure that we give you the best experience on our website. If you continue to use this site we will assume that you are happy with it.